



EDITOR’S NOTE: The author of this article would like to acknowledge that it was prepared with assistance from ChatGPT.
I had vascular surgery recently. The anticipated overnight care resulted in a five-day inpatient stay, which was consistent with the typical length of stay associated with the assigned Diagnosis-Related Group (DRG).
But my surgery and stay were longer than initially expected due to the size of the specimen they removed from my blood vessel, my co-morbidities, and a reaction to the adhesives and CHG wipes, respectively. My time in the operating room (OR) was approximately five hours. The vascular surgeon was in the OR for approximately 4 hours. My surgeon billed $4,300, and Medicare allowed $735.
Somehow, $184 an hour for a vascular surgeon doesn’t seem appropriate, especially when one considers that the $735 also included the discharge and post-surgery follow-up visits in the global period. These diluted the $184 rate even more.
The Medicare Physician Fee Schedule (MPFS) is a resource-based payment system. Medicare does not generally pay any surgeon or physician based on the provider’s charge or the patient’s diagnosis alone. Instead, the Centers for Medicare & Medicaid Services (CMS) assigns each covered CPT®/HCPCS service a relative value, adjusts it for local costs, converts it to dollars, and then applies billing and payment rules. CMS publishes Relative Value Units (RVUs) and payment-policy indicators for more than 10,000 services in its MPFS files and lookup tool (see: https://www.cms.gov/medicare/physician-fee-schedule/search/documentation).
How the Fee Schedule is Developed
Each year, CMS publishes a proposed rule, receives public comments, and issues a final rule establishing the next calendar year’s fee schedule.
The process generally works as follows:
- CPT codes describe the services.
The American Medical Association’s (AMA’s) CPT Editorial Panel creates and revises CPT codes. HCPCS Level II codes are maintained by CMS for certain additional services and supplies. - Clinical specialties recommend relative values.
The AMA/Specialty Society Relative Value Scale Update Committee (RUC) collects information from specialty societies regarding physician time, intensity, technical skill, mental effort, risk, staff, supplies, and equipment. For vascular procedures, the Society for Vascular Surgery and related specialties may participate in this process. - CMS reviews the recommendations.
CMS is not required to accept the RUC’s recommendations. It may use specialty survey data, claims data, time studies, comparisons with other services, clinical literature, and its own analyses. - CMS assigns RVUs and other payment indicators.
Each service receives RVUs for physician work, practice expense, and malpractice expense (see component descriptions below). CMS also determines whether rules involving global surgery, multiple procedures, bilateral procedures, assistant surgeons, co-surgeons, and professional/technical components apply.
| Component | What it represents |
| Physician Work RVU | Physician time, technical skill, physical and mental effort, clinical judgment, stress, and risk. |
| Practice Expense RVU | Clinical staff, medical supplies, equipment, office space, administrative overhead, and other operating costs. |
| Malpractice RVU | Relative professional-liability expense associated with the service and specialty. |
Practice expense is notable. Physicians practicing in metropolitan areas likely have higher expenses than those in rural areas. However, ensuring availability of practice staff may be more challenging in rural areas.
The simplified payment formula is the following:
- The three RVU components as described above; and
- Geographic adjustments.
Each RVU component is multiplied by its own Geographic Practice Cost Index (GPCI). Consequently, the same CPT code may have a different allowed amount in St. Louis, Kansas City, the rest of Missouri, Chicago, or New York.
The payment locality is generally based on where the service was furnished. Indices change annually.
For 2026, to offer an example, the Medicare GPCIs are:
| Missouri Medicare locality | Work GPCI | Practice expense GPCI | Malpractice GPCI |
| Metropolitan St. Louis | 1.000 | 0.952 | 1.002 |
| Rest of Missouri | 1.000 | 0.862 | 0.974 |
Source: CMS’s January 2026 Physician Fee Schedules at: https://www.cms.gov/medicare/payment/fee-schedules/physician/pfs-relative-value-files/rvu26a.
- Physician work: There is no payment difference. The calculated work GPCIs were 0.988 for St. Louis and 0.976 for the rest of Missouri, but the statutory 1.000 work GPCI floor raises both to 1.000 for payment.
- Practice expense: St. Louis’s index of 0.952 is approximately 10.4 percent higher than the rest-of-Missouri index of 0.862.
- Malpractice expense: St. Louis’s index of 1.002 is approximately 2.9 percent higher than the rest-of-Missouri index of 0.974.
The payment calculation, therefore, is:
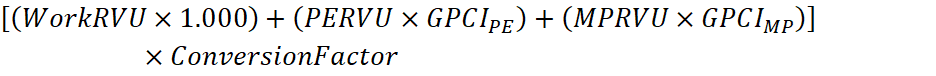
Consequently, a service performed in metropolitan St. Louis generally receives a higher geographically adjusted amount than the same service performed in the rest of Missouri (excluding Kansas City). The exact percentage difference depends on the CPT code’s mix of work, practice-expense, and malpractice RVUs. A procedure with substantial practice-expense RVUs will show a larger difference than a professional service composed primarily of physician-work RVUs.
The geographically adjusted RVUs are multiplied by a national dollar conversion factor. For 2026, CMS established two conversion factors:
- $33.57 for qualifying participants in an Advanced Alternative Payment Model (APM); and
- $33.40 for clinicians who are not qualifying APM participants.
The 2026 amounts include statutory updates, a temporary 2.5-percent increase enacted for 2026, and a budget-neutrality adjustment. See the CMS 2026 PFS final-rule summary.
So, what ultimately determines payment on a vascular surgeon’s claim?
The formula produces the starting fee-schedule amount. Actual payment depends on several additional factors.
A. The Exact CPT/HCPCS Procedure Reported
In my case, I had vascular surgery, which encompasses various different services, including:
- Office and hospital evaluation and management (E&M) visits;
- Open arterial and venous operations;
- Endovascular interventions;
- Catheter placement;
- Angiography and radiologic supervision and interpretation;
- Dialysis-access procedures;
- Venous ablation;
- Noninvasive vascular diagnostic studies; and
- Debridement and wound-related services.
Each code has its own RVUs and payment indicators. The fact that the physician is a vascular surgeon does not, by itself, establish the payment. The specific service code is the starting point.
In my case, I hoped the surgeon considered adding modifier 22. Pre-operatively, the surgeon anticipated an overnight stay, which I suspect would have been observation status or “outpatient in a bed.” This, coupled with my co-morbidities and the unexpectedly large specimen, might be relevant if it substantially increased the surgeon’s work and was clearly documented. The reaction to adhesives or CHG wipes would not ordinarily support modifier 22 unless it directly increased the procedural work performed by the surgeon. It did not, since it occurred post-operatively, but this does affect the facility coding.
Medicare ordinarily pays according to the typical work reflected in the assigned RVUs. A longer-than-usual operation does not automatically generate additional payment. However, when the physician’s work is substantially greater than typically required, modifier 22 may be appended to the procedure code.
Documentation should explain:
- Why the procedure was unusually difficult;
- The condition or anatomy creating the difficulty;
- The additional physician work required;
- Additional operative time, compared with the usual procedure;
- Technical difficulty, intensity, or risk; and
- How the unusual circumstances affected performance of the procedure.
The Medicare Administrative Contractor (MAC) reviews the documentation and determines whether additional payment is justified. Modifier 22 does not guarantee increased payment, and it does not bypass a National Correct Coding Initiative (NCCI) edit. The CMS NCCI Policy Manual is available online at https://www.cms.gov/files/document/medicare-ncci-policy-manual-2024-chapter-1.pdf
B. Facility versus Nonfacility Setting
This is particularly important for vascular services.
- Facility rate: Used when the surgeon performs the service in a hospital, hospital outpatient department, or usually, an ambulatory surgical center (ASC). Because the facility bears the staff, equipment, and supply costs, the surgeon receives a lower practice-expense component.
- Nonfacility rate: Used when the service is performed in the physician’s office and the practice bears the staff, equipment, and supply costs. The physician payment may therefore be considerably higher.
A higher office payment is not necessarily additional profit; it is intended to cover the office’s equipment, supplies, technicians, space, maintenance, and overhead.
Perhaps the rate my surgeon received was impacted by the setting, since it was in the hospital, and therefore, paid at the facility rate.
C. Professional versus Technical Components
Some vascular diagnostic tests have:
- A professional component, such as interpretation and report, usually reported with modifier 26;
- A technical component, covering equipment, supplies, and technical personnel, usually reported with modifier TC; or
- A global diagnostic service, when the same entity furnishes both components.
For example, when a vascular surgeon interprets a duplex study performed with hospital equipment, the surgeon generally receives only the professional-component payment. If the surgeon’s office owns the equipment and performs the test, the practice may receive the global or technical and professional payments, subject to supervision, enrollment, coverage, and coding requirements.
D. Bundling of Endovascular Services
Many endovascular codes bundle services that historically may have been separately reported. Depending on the particular code family, the primary procedure may include such components as:
- Accessing the vessel;
- Introducing and manipulating catheters;
- Crossing the lesion;
- Imaging related to performing the intervention;
- Radiologic supervision and interpretation;
- Completion angiography; and
- Closure of the access site.
Other services may be separately reportable only when performed in a different vascular territory, through a separate encounter, or for an independently medically necessary diagnostic purpose. Correct application of CPT coding rules and NCCI edits is therefore critical.
E. Multiple-Procedure Reductions
Vascular surgeons frequently perform multiple procedures during one operative session. Medicare usually ranks procedures by allowed amount and pays:
- The highest-valued eligible procedure at 100 percent; and
- Other eligible procedures at a reduced percentage – often 50 percent, depending on their multiple-procedure indicators.
The precise result depends on each code’s indicator and whether the services are bundled. CMS describes these rules in its PFS status-indicator guidance. (See: https://www.cms.gov/help/status-indicators)
F. Bilateral Procedures
If a service is performed on both sides, payment depends on the code’s bilateral-surgery indicator and the way the claim is submitted. Modifier 50, or RT and LT, where appropriate, does not automatically produce double payment. Some procedures qualify for the standard bilateral adjustment, some are inherently bilateral, and others are priced separately by side.
G. Global Surgical Package
Many major vascular operations have a 90-day global period. The surgical payment generally includes:
- Certain preoperative services;
- The operation itself;
- Routine postoperative management; and
- Related postoperative visits by the surgeon or another physician in the same group and specialty.
Accordingly, the surgeon does not receive a separate payment for every routine postoperative encounter. Medicare also has 0-day and 10-day global designations for other procedures. CMS confirms that most covered surgical procedures with a global period include postoperative visits in the original payment. See CMS Global Surgery Data Collection at: https://www.cms.gov/medicare/payment/fee-schedules/physician/global-surgery-data-collection.
H. Modifiers May Affect Payment When:
- The decision for major surgery occurs shortly before surgery (modifier 57);
- A significant, separately identifiable E&M service is performed with a minor procedure (modifier 25);
- An unrelated service is performed during the global period (modifier 24);
- A return to the operating room is required (modifier 78);
- An unrelated procedure is performed during the global period (modifier 79); or
- Postoperative care is formally transferred (modifiers 54 and 55).
Documentation must support the modifier.
I. Assistant Surgeon, Co-surgeon, and Team-Surgeon Rules
Complex vascular cases sometimes require an assistant, co-surgeon, or surgeons from different specialties. Payment depends on the code-specific indicator and the modifier:
- 62 – co-surgeons
- 66 – surgical team
- 80, 81, 82, or AS – assistant at surgery arrangements
Not every procedure permits separate payment for an assistant or co-surgeon. CMS’s fee-schedule files contain the applicable indicators. CMS has stated that assistant-at-surgery services are potentially payable only when the procedure’s indicator permits payment and the assistant is medically necessary. See CMS assistant-at-surgery guidance at: https://www.cms.gov/data-research/monitoring-programs/medicare-fee-service-compliance-programs/medicare-fee-service/2a318-assistant-surgery-services-billed-without-correct-payment-modifiers-incorrect-coding.
J. Coverage and Medical Necessity
Having a CPT code and fee-schedule amount does not guarantee payment. The service must:
- Be a Medicare benefit;
- Meet national and local coverage requirements;
- Be reasonable and necessary;
- Have a covered diagnosis when required;
- Meet frequency and supervision requirements;
- Be properly documented; and
- Pass NCCI and medically unlikely edit checks.
K. The physician’s actual charge and assignment status
For a participating physician accepting assignment, Medicare bases payment on the lower of the submitted charge or the Medicare fee-schedule allowed amount.
After the beneficiary meets the Part B deductible:
- Medicare generally pays 80 percent of the allowed amount; and
- The patient or supplemental insurer is responsible for the remaining 20 percent.
A nonparticipating physician’s Medicare-approved amount is generally 95 percent of the participating amount, with balance billing restricted by the limiting-charge rules. CMS explains that the limiting charge generally equals 115 percent of the nonparticipating payment amount in its PFS documentation at: https://www.cms.gov/medicare/physician-fee-schedule/search/documentation.
L. MIPS or Advanced APM adjustments
The final remittance can also be affected by the Quality Payment Program (QPP).
- A vascular surgeon subject to the Merit-Based Incentive Payment System (MIPS) can receive a positive, neutral, or negative adjustment based on an earlier performance year.
- For the 2026 payment year, the MIPS adjustment is based on 2024 performance, with a maximum negative adjustment of 9 percent. Actual positive adjustments are constrained by budget neutrality.
- A qualifying Advanced Alternative Payment Models (APM) participant uses the slightly higher 2026 qualifying-APM conversion factor.
Other adjustments, such as sequestration, claims-level reductions, or participation in certain payment models, may further affect the amount shown on the remittance.
A Surgery Example
Suppose a surgeon performs a major operation in a hospital:
- The CPT code carries work, facility practice-expense, and malpractice RVUs.
- Each RVU is adjusted by the GPCI for the location where the operation occurred.
- The resulting RVUs are multiplied by the applicable 2026 conversion factor.
- Medicare applies any applicable multiple-procedure, bilateral, co-surgeon, or assistant-surgeon rules.
- The payment includes routine services contained in the 90-day global package.
- The claim is then affected by assignment, beneficiary cost sharing, MIPS/APM status, and any claims-level adjustments.
The hospital receives a separate payment under the Inpatient Prospective Payment System (IPPS) or Outpatient Prospective Payment System (OPPS) for its facility services. That hospital payment is not part of the surgeon’s MPFS professional payment.
For a physician and, in particular, a surgeon, Medicare payment is primarily determined by: the exact combination of CPT codes, facility versus office setting, bundling of surgical services, multiple-procedure reductions, global-period rules, and professional-versus-technical billing.
The question remains: would an adjustment to payment rates close the physician shortage gap?
First, is there a physician shortage?
There is a current shortage in many communities and specialties, and federal projections indicate that it will worsen.
- Approximately 20 percent of the U.S. population lives in a federally designated primary-care Health Professional Shortage Area. Shortages are particularly pronounced in rural and underserved urban communities. Health Workforce Shortage Areas
- The Health Resources and Services Administration (HRSA) projects a national shortage of approximately 141,160 full-time-equivalent physicians by 2038, including about 70,610 primary-care physicians. Nonmetropolitan areas are projected to experience especially severe shortages. HRSA, State of the U.S. Health Care Workforce, 2025 at: https://bhw.hrsa.gov/sites/default/files/bureau-health-workforce/data-research/State-of-US-Health-Care-Workforce-2025.pdf
- A separate Association of American Medical Colleges (AAMC) model projects a shortage of between 13,500 and 86,000 physicians by 2036, including shortages in both primary and specialty care. The difference between the HRSA and AAMC estimates reflects different methodologies and assumptions, not disagreement that shortages exist. AAMC physician workforce projections are available at: https://www.aamc.org/data-reports/workforce/report/physician-workforce-projections.
The problem is partly an absolute shortage, but also one of distribution and availability. A community may have physicians on paper, but still lack timely access because physicians are concentrated elsewhere, work fewer clinical hours, have closed panels, or practice in specialties that do not match the population’s needs.
Important contributors include:
- Growth and aging of the population;
- Retirement and burnout among physicians;
- Limited residency-training positions;
- Rural and underserved-area maldistribution;
- Increasing demand for primary, geriatric, behavioral health, and specialty services; and
- Administrative burden and reduced time available for direct patient care.
Are physicians opting out of Medicare?
Some are, but there is not currently evidence of a broad nationwide exodus from Medicare.
Only about 1 percent of non-pediatric physicians formally opted out of Medicare in 2024. The rate was considerably higher among certain specialties: approximately 8.1 percent of psychiatrists, 4.5 percent of plastic and reconstructive surgeons, and 3.2 percent of neurologists, for example. Kaiser Family Foundaion (KFF) analysis of CMS opt-out data is available at: https://www.kff.org/medicare/how-many-physicians-have-opted-out-of-the-medicare-program/
“Opting out” has a specific Medicare meaning: the physician files an affidavit with Medicare, does not bill Medicare for covered services, and uses private contracts with Medicare beneficiaries. This differs from a physician who:
- Remains enrolled but is nonparticipating;
- Accepts assignment only on selected claims;
- Limits the percentage of Medicare patients in the practice;
- Continues treating established Medicare patients, but does not accept new ones; and
- Accepts Original Medicare but does not participate in a particular Medicare Advantage (MA) network.
These less-visible restrictions are probably more important to patients than the formal opt-out rate.
Are Medicare patients having difficulty finding physicians?
Nationally, Medicare beneficiaries’ access remains relatively strong. MedPAC’s 2025 survey found that Medicare beneficiaries generally reported access that was as good as, or better than, that reported by privately insured people. Nevertheless, some beneficiaries experienced long waits or difficulty finding a new primary-care physician or specialist. MedPAC, Health Care Spending and the Medicare Program, July 2026 at: https://www.medpac.gov/wp-content/uploads/2026/07/July2026_MedPAC_DataBook_Sec7_SEC.pdf
Thus, both of the following statements can be true:
- Most physicians continue to care for Medicare patients, and national Medicare access indicators remain reasonably favorable.
- Individual communities, especially in rural areas and specialties such as psychiatry, primary care, geriatrics, neurology, and some surgical specialties, can have serious access problems.
Bottom line
The United States does have a physician shortage, but it is unevenly distributed by geography and specialty. Physicians are not formally opting out of Medicare in large numbers; however, growing numbers may be limiting new Medicare patients, narrowing their Medicare panels, leaving independent practice, or declining certain Medicare Advantage contracts. Consequently, the formal 1-percent opt-out statistic may understate the access pressure experienced by patients locally.
The shortage is not necessarily tied to payment rates, although for a few specialties, the non-covered services may be a reason for transitioning to non-participating status. However, Medicare payment rates are one factor affecting physician practice viability, willingness to accept new Medicare patients, and decisions about specialty, location, employment, and retirement. In particular, the higher rates paid for metropolitan-based practices versus rural practices do little to incentivize physicians to locate and serve the rural communities.
However, payment rates alone do not explain the physician shortage, and an across-the-board payment increase would not eliminate it. The shortage also reflects the aging population, physician retirements, geographic maldistribution, limited residency capacity, lengthy training requirements, burnout, administrative burden, and differences in demand among specialties.
Targeted and enhanced payment policies – particularly for primary care, behavioral health, shortage areas, and services that may be perceived as potentially undervalued physician work –may improve access more effectively than an undifferentiated increase in all MPFS.



















